


Why They Fail ... and the Simple Key to Success!
Subscribed: 2Played: 16
Subscribe

© 2025 Six Sigma Development Solutions, Inc.
Description
Tired of watching continuous improvement efforts crash and burn? So are we. "Why They Fail" dives headfirst into the brutal truth behind failed Lean Six Sigma deployments, exposing the myths, the mistakes, and the outright absurdities that plague organizations worldwide. Forget the sugar-coated success stories—we're here to dissect the disasters, from executives who think training is optional to lone Green Belts drowning in unrealistic expectations. But it's not all doom and gloom. We'll also reveal the surprisingly simple key to unlocking sustainable success: ditching the quick fixes and building a rock-solid foundation. Buckle up, because this podcast is a no-holds-barred, reality check that will transform the way you think about continuous improvement.
29 Episodes
Reverse
The Fix Worked, Culture Didn't: A VA Door to Doc Story
Five minutes for one doctor. Over 400 minutes for another. Same emergency room, same shifts. That is the scale of door to doc variation one Lean Six Sigma team found inside a Veterans Affairs hospital. However, the real story is what happened next. They fixed it, and then the fix died the moment the team walked away.
In this episode of the Why They Fail Podcast, Kevin Clay sits down with Lacee Koerner (MSN, RN, CEN), an emergency room and quality nurse. Together, they walk through an honest account of a project that worked on paper but failed in practice.
TACKLING DOOR TO DOC VARIATION IN THE EMERGENCY ROOM
At first, Lacee and her team set out to reduce Left Without Being Seen rates. However, during their early Gemba walks, they found something uncomfortable. The numbers leadership trusted were easy to bend through simple workarounds.
Therefore, the team changed direction. Instead of chasing a metric staff could shape, they moved to door to doc variation. As a result, they captured what was really happening rather than what the reports claimed.
Next, they ran a careful Measurement System Analysis and applied statistical process control. Consequently, the swings became visible. One doctor answered in five minutes. Another took more than 400. Once they found those outliers and set up controls, response times dropped in a way the data could prove.
WHY GREAT PROCESS FIXES GO DEAD ON ARRIVAL
So the fix worked. Nevertheless, it did not last. In this candid talk, Lacee explains why the project went dead on arrival once her team stepped back.
Because there was no supervisor buy-in, no steady backing from leaders, and no daily support system, the gains faded fast. Within weeks, the department drifted back to old habits. In other words, nothing held the change in place.
Furthermore, the staff were hearing two messages at once. On one hand, leaders asked for strict compliance. On the other hand, they asked nurses to speak up and own the work. Therefore, this episode lands on a hard truth. Data and tools can solve the technical problem. Only leaders and culture can keep it solved.
KEY TAKEAWAYS
Above all, these lessons separate a fix that holds from one that quietly slips away.
First, uncontrolled door to doc variation hurts patient flow and care quality. Second, a careful measurement system analysis stops teams from trusting numbers that have been shaped. Third, top-down orders without supervisor buy-in create pushback, and eventually the project falls apart. Fourth, even a proven win will go dead on arrival unless something is built to hold it. Finally, lasting improvement happens when leaders match what they ask for with how they actually behave.
FREE BOOK
Over 90% of continuous improvement programs fail within eighteen months. In his book, Kevin explains exactly why, and what to do instead. Therefore, if your last project slipped back, this is a good place to start. Get a free copy of "Why They Fail and the Simple Key to Success" here:
Chapters
(00:00:00) - Intro and Framing the Contradiction(00:01:15) - Meet Lacey Kerner and Her CI Journey(00:04:03) - Does VA Culture Embrace Data?(00:05:36) - Bureaucracy and Data Access Struggles(00:07:22) - Frontline Nurses' Resistance to the Project(00:09:31) - Lack of Infrastructure and Sustainment Challenges(00:11:43) - Cutting Through Red Tape for Data(00:13:57) - Executive Sponsorship and Leadership Buy-in(00:16:07) - Top-Down vs Frontline Empowerment Paradox(00:18:47) - Did the Improvements Stick?(00:19:34) - Defining the Door-to-Doc Project(00:22:58) - Data Analysis Errors and Discovering Variability(00:25:13) - Wild West Variation and Finding Focus(00:26:37) - Closing Thoughts and Show Wrap-up

Stop Blaming Workers: Fix Broken Systems and Bad Metrics
Fire the employee who made the mistake and the next person in that seat will make the exact same mistake. That is the uncomfortable truth behind most operational failures. Leaders who want real improvement must stop blaming workers for mistakes and start diagnosing the systems that produce them.
In this episode of the Why They Fail Podcast, Kevin Clay sits down with continuous improvement expert and author Mark Graban. Together, they explore Dr. W. Edwards Deming's management philosophy, the stark contrast between command-and-control leadership and the Toyota Production System, and why treating Lean as a cost-cutting gimmick always fails.
WHY LEADERS MUST STOP BLAMING WORKERS FOR MISTAKES
When organizations operate under a culture of fear, employees learn one lesson quickly. Transparency leads to punishment. Consequently, workers begin hiding defects, delaying communication, and smoothing over metric variation just to protect themselves.
Dr. Deming demonstrated that roughly 94% of all workplace problems are built directly into the system. High-level decisions about suppliers, equipment maintenance, staffing levels, and management expectations dictate performance far more than individual effort ever could.
Therefore, firing an employee without fixing the broken workflow accomplishes nothing. The role stays the same. The process stays the same. The failure repeats. Moving forward requires leaders to stop blaming workers for mistakes and build genuine psychological safety at every level of the organization.
LESSONS FROM GM, NUMMI, AND THE RED BEAD GAME
Mark Graban reflects on his early career at General Motors, where toxic management practices produced catastrophic quality issues and dismal morale. However, GM's joint venture with Toyota at the NUMMI plant told a completely different story. The same workforce, under a collaborative management system, achieved world-class results.
The famous Deming Red Bead Game illustrates this vividly. When the system itself forces defects, no amount of slogans, targets, or yelling will change the outcome. Instead of reacting emotionally to daily metric fluctuations, effective leaders use process behavior charts. As a result, they can distinguish normal system noise from genuine statistical signals worth acting on.
BUILDING A TRUE LEAN MANAGEMENT CULTURE
Lean is not a toolbox for short-term headcount reduction. When executives reduce it to cost-cutting, they sacrifice employee engagement, product quality, and workplace safety in the process.
True operational excellence pairs Lean problem-solving with data-driven Six Sigma analytics. Together, they eliminate unnecessary complexity and remove waste at the root. Furthermore, when leaders listen to the process instead of blaming people, they unlock sustainable capacity, higher quality, and lasting organizational success.
ABOUT THE GUEST: MARK GRABAN
Mark Graban is an internationally recognized author, speaker, consultant, and entrepreneur who works with leaders to improve qual...
Chapters
(00:00:00) - Why They Fail(00:00:53) - Why They Fail: The Lean Startup(00:09:38) - The Toyota Way: A Culture of Excellence(00:13:20) - GM's 'command and control' culture(00:19:03) - GM's 'Lean' Program(00:23:59) - Does Lean Matter?(00:31:10) - How to Prevent and Learn From Mistakes?(00:36:38) - Control Charts for Process Behavior Charts(00:43:10) - Why They Fail
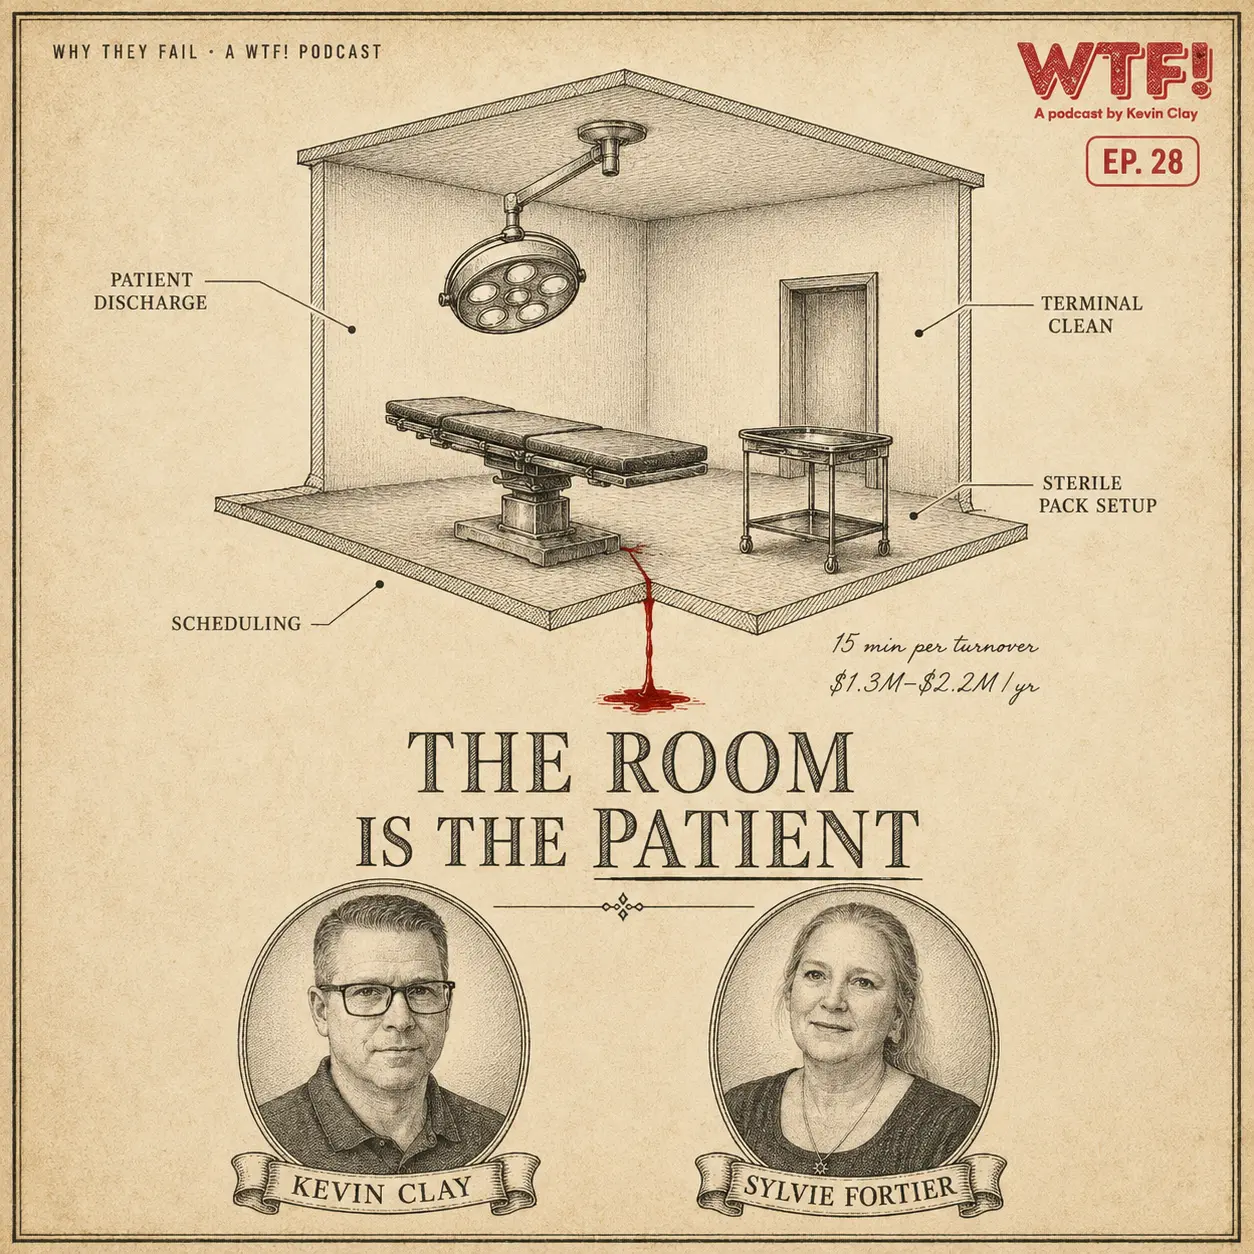
Surgical Pressure Cooker: Stop Wasting Capacity in ASCs
Fifteen minutes between cases does not sound like much. However, across a standard daily schedule it compounds into 150 minutes of lost room capacity. That translates to an annual revenue bleed between $1.3 million and $2.2 million. Eliminating operational friction in surgery centers is one of the fastest margin recoveries available to any ASC leadership team.
In this episode of the Why They Fail Podcast, Kevin Clay sits down with Sylvie Fortier, an operations leader whose career began during the foundational rollout of Six Sigma across Motorola's global enterprise. Together, they examine how hidden delays between cases quietly drain both revenue and organizational culture.
UNDERSTANDING OPERATIONAL FRICTION IN SURGERY CENTERS
Ambulatory surgery centers function like high-stakes pressure cookers. Top surgeons operate with extreme clinical precision every single day. However, the true bottleneck is rarely the surgical procedure itself.
Instead, uncoordinated turnover minutes cost facilities thousands of dollars daily. The gap sits between patient discharge, terminal cleaning, and sterile pack setup. Consequently, a delay of just 15 minutes per case costs a typical facility between $5,500 and $9,000 every day.
Furthermore, the root cause is usually information asymmetry rather than individual performance. Scheduling, anesthesia, and materials management often operate with different information at different times. Therefore, the friction is architectural, not personal.
WHY MORE DATA IS NOT THE SOLUTION
When surgical turnarounds lag, leadership often responds by tracking more variables. They purchase new dashboard software and add more metrics to the reporting stack. However, adding data to an already overwhelmed environment creates decision paralysis rather than operational control.
Execution rarely stalls because of missing data or missing standard operating procedures. Instead, processes break down because leadership lacks the filters needed to separate actionable signals from background noise. As a result, teams see everything and act on nothing.
ALIGNING LEADERSHIP WITH HOSHIN KANRI
Most operational breakdowns stem from human and strategic misalignment rather than simple process errors. In healthcare specifically, clinical founders focus on case complexity and patient outcomes. Meanwhile, financial partners prioritize fiscal margins and throughput.
Therefore, bridging that gap requires a visual strategy tool. Hoshin Kanri and the single-page X Matrix map strategic goals, tactical projects, and resource ownership onto one agreed document. When leadership can see all three on a single page, cross-departmental friction drops sharply. Consequently, teams establish genuine operational sovereignty over their own outcomes.
ABOUT THE GUEST: SYLVIE FORTIER
Sylvie Fortier is the founder of Phoenix Praxis, where her work centers on a single idea: making the invisible visible. She helps ambulatory surgery centers and complex organizations surface the operational friction that neve...
Chapters
(00:00:00) - Why They Fail(00:01:14) - Why They Fail: Six Sigma and Continuous Improvement(00:06:01) - How to Build a Continuous Improvement Culture(00:07:10) - Operational Friction Points in Ambulatory Surgery Centers(00:12:27) - How to Get the Leadership Group On the Same Page(00:18:30) - Healthcare Operational Data Overwhelm(00:21:44) - The Importance of Outside Perspectives(00:22:51) - Choosing a food with a clean label(00:26:47) - How to Eliminate Operational Friction in Surgery Centers

Ditch The Rubber Stamp: Fixing Broken Risk With KPIs
Your quarterly risk assessment is reporting on problems from three months ago. By then the process has already changed and the root cause is long gone. Proactive risk management with KPIs replaces that lag with real-time operational visibility.
In this episode of the Why They Fail Podcast, Kevin Clay sits down with risk management specialist Joanne Bronish to examine why traditional compliance programs fail to deliver meaningful value. Together, they uncover how disconnected corporate structures turn risk management into an expensive checklist exercise. Furthermore, they explore how leaders can build real-time alignment across every operational function.
WHY TRADITIONAL RISK PROGRAMS FAIL
Most enterprise risk programs rely heavily on documentation, static controls, and periodic audits. However, audits typically occur months after a process breakdown has already happened. By the time an issue is flagged, the underlying workflow has changed. Consequently, teams end up reacting to outdated symptoms rather than addressing actual root causes.
As a result, compliance assessments often become nothing more than a quarterly rubber-stamp exercise. Because employees see little operational return on investment, engagement drops quickly. Therefore, the risk function transforms into its own isolated silo, disconnected from the daily work it is supposed to protect.
Moreover, bloated governance structures become an expensive internal tax. Organizations invest millions in complex control frameworks and receive very little measurable value in return.
BUILDING PROACTIVE RISK MANAGEMENT WITH KPIS
To build genuine operational resilience, organizations must connect quality, risk, and process efficiency. These three areas are not separate initiatives. Instead, they examine the exact same processes through different functional viewpoints.
When organizations establish proactive risk management with KPIs, they gain real-time visibility into process variance. Tracking cascading leading indicators allows teams to spot statistical drift early. Consequently, they fix potential bottlenecks long before those bottlenecks trigger regulatory penalties or customer-facing defects.
Additionally, this approach bridges the persistent gap between executive tone at the top and front-line execution. When metrics cascade cleanly from strategic objectives down to operator-level indicators, everyone can see how their work connects to organizational risk exposure.
KEY TAKEAWAYS
Applying these principles is what separates a risk function that protects the business from one that simply documents its failures.
First, traditional risk programs act as reactive end-of-line inspections that fail to catch real-time operational drift. Second, bloated governance systems become an expensive internal tax draining resources without delivering measurable ROI. Third, risk, quality, and inefficiency examine the exact same process workflows and must be aligned together. Fourth, cascading key performance indicators provide early warning signals well before major failures occur. Fifth, long-t...
Chapters
(00:00:00) - Why Continuous Improvement Efforts Fail(00:00:56) - Why They Fail: Risk Management Programs(00:07:55) - How to Build a More Engaged Organization(00:08:58) - Why Do Risk Management Programs Turn Into a Rote Compliance Checklist(00:15:35) - Quality, Inefficiencies and Regulatory Risk(00:24:42) - Risk Management of KPIs(00:26:54) - Why They Fail

How 32 Minutes Unlocked $64K in Operational Waste
Uncovering process mapping hidden cost savings does not require complex statistics or months of tedious analysis. Often, powerful cost reduction is hiding right under your nose. In just 32 minutes, a simple visual workflow exercise surfaced $64,000 in operational waste at a single Dallas eye clinic.
In this episode of the Why They Fail Podcast, Kevin Clay sits down with Ben Morley, a former Air Force C-17 pilot and experienced instructor. Together, they explore how basic visual tools instantly reveal profit leaks that expensive software and long consulting engagements often miss entirely.
THE POWER OF PROCESS MAPPING HIDDEN COST SAVINGS
Many corporate teams struggle with massive project scopes. They try to solve every problem at once. However, when you narrow your scope, you achieve rapid and meaningful results. Ben shares how applying simple visual workflow tools uncovered $64,000 in hidden waste in just 32 minutes. Consequently, the team turned an unexpected bottleneck into an immediate financial victory.
This is the core of process mapping hidden cost savings. You do not need advanced analytics to start. Instead, you need a clear picture of how work actually flows. Once a team sees the real process on a wall, the waste becomes obvious. Therefore, the first improvement often pays for the entire initiative.
APPLYING FLIGHT DECK DISCIPLINE TO CORPORATE OPERATIONS
In aviation ground operations, strict checklist protocols and explicit communication handoffs are mandatory. Therefore, when pilots transition between tasks, nothing is left to chance. Ben learned this discipline flying high-stakes polar missions to McMurdo Station in Antarctica.
In contrast, corporate teams often operate in isolated functional silos. As a result, operational friction builds silently. This friction causes delivery delays, inaccurate data tracking, and severe profit leaks. By introducing ground operations discipline to everyday workflows, leaders eliminate communication barriers. Consequently, they capture significant process mapping hidden cost savings that were invisible before.
UNLOCKING CAPACITY WITHOUT ADDING OVERHEAD
Rigorous data analysis allows organizations to discover hidden process capacity without spending extra money. Statistical process control charts help managers separate true operational signals from random noise. As a result, businesses dramatically boost output without buying new machinery or hiring additional staff.
In one example, a disciplined focus on existing capacity moved production output from 32,000 units to 60,000 units per month. No new equipment. No added headcount. Just a clear view of the process and the discipline to act on what the data revealed.
ABOUT THE GUEST: BEN MORLEY
Ben Morley is a retired U.S. Air Force Lieutenant Colonel who spent 27 years flying the C-17 and C-141, landing on all seven continents and leading teams through high-stakes operations before he ever set foot in a boardroom. When the uniform came off, he had to answer the same question he now helps his clients answer: who am I witho...
Chapters
(00:00:00) - Why Continuous Improvement Efforts Fail(00:01:12) - Why They Fail: Continuous Improvement in the Military(00:03:42) - What was the absolute catalyst that flipped you from actively avoiding butcher block(00:09:11) - The Never-Ending Project(00:09:59) - What Makes a Normal Mission Impossible?(00:13:55) - The Secret to Teaching a Continuous Improvement Course(00:20:35) - Slow Startup: The Lean Revolution(00:22:35) - 3 Rules for Ground Operations Deserves(00:26:13) - How to Manage Ground Operations(00:28:36) - Why They Fail

Comments

Download from Google Play

Download from App Store
 United States